


Quick answer
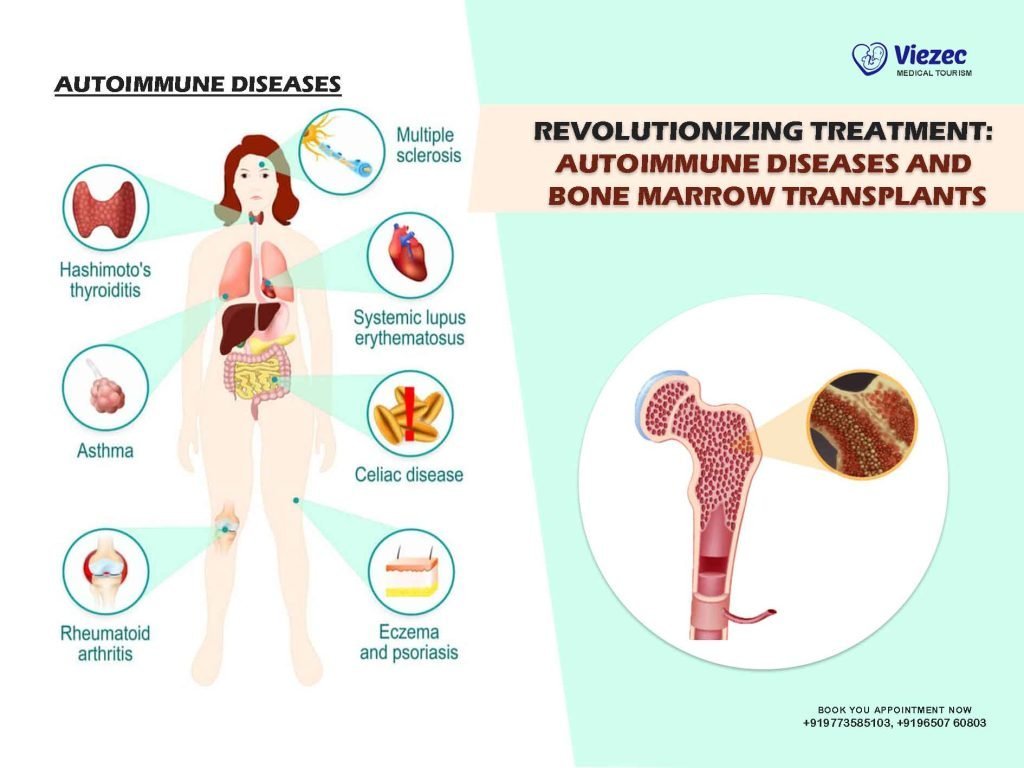
Hematopoietic stem cell transplantation (HSCT), commonly called bone marrow transplant, is a serious medical procedure used for select, severe cases of certain autoimmune diseases — most notably multiple sclerosis and systemic sclerosis (scleroderma) — where it has shown significant benefit in randomized controlled trials compared to standard treatment. It works by using chemotherapy to eliminate the existing, disease-causing immune system, then reinfusing the patient’s own previously collected stem cells to rebuild a new immune system. This is fundamentally different from, and carries substantially more risk than, the mesenchymal stem cell (MSC) infusions discussed for other conditions on this site — it involves real treatment-related mortality risk and is reserved for carefully selected, severe cases at specialized transplant centers, not offered as a general or low-risk option.
What is HSCT, and how is it different from other stem cell approaches?
HSCT (autologous hematopoietic stem cell transplantation) works in three stages:
- Stem cell collection — the patient’s own hematopoietic (blood-forming) stem cells are collected from peripheral blood
- Immunoablative conditioning — high-dose chemotherapy (sometimes combined with other agents) is used to eliminate the existing immune system, including the disease-causing immune cells
- Stem cell reinfusion — the previously collected stem cells are reinfused, allowing a new immune system to develop
This is a meaningfully different and more intensive procedure than mesenchymal stem cell (MSC) infusions used for other conditions discussed elsewhere on this site, which do not involve chemotherapy or immune system ablation. HSCT carries real procedural risks, including infection during the period of immune reconstitution and a treatment-related mortality risk generally cited in the range of 1–2% in modern series, which is why it’s reserved for select, severe, and typically treatment-refractory cases rather than offered broadly.
What does the evidence show, by condition?
Multiple sclerosis — the strongest evidence
The MIST trial, a randomized controlled trial, compared HSCT against standard disease-modifying therapies in patients with relapsing multiple sclerosis and found HSCT was associated with significantly better outcomes, including a substantially lower rate of disease progression over the follow-up period. This is considered one of the most robust pieces of evidence for any regenerative approach discussed on this site — a properly randomized trial with a clear, statistically significant result.
Systemic sclerosis (scleroderma) — also strong, randomized evidence
The ASTIS trial, an international randomized controlled trial, compared HSCT against cyclophosphamide (a standard immunosuppressive treatment) in patients with severe systemic sclerosis and found HSCT was associated with significantly better long-term, event-free survival, despite higher treatment-related mortality in the first year following the procedure. This trade-off — better long-term outcomes against increased early risk — is central to why patient selection for this procedure is so important.
Crohn’s disease — more limited and mixed
The ASTIC trial evaluated HSCT specifically for refractory Crohn’s disease and found that while some patients showed clinical and endoscopic improvement, the trial did not meet its primary endpoint of sustained disease remission without ongoing treatment, and treatment-related toxicity was higher than anticipated. This is a meaningfully different, more cautious evidence picture than what’s seen in MS and systemic sclerosis, and it’s important not to blur the two together.
Who is actually considered for this procedure?
Given the real risks involved, HSCT for autoimmune disease is generally considered only for patients who:
- Have severe disease that has not responded adequately to standard treatments
- Are otherwise in reasonably good health to tolerate an intensive procedure
- Have a disease type and severity profile matching what’s been studied in the strongest trials (particularly relevant for MS and systemic sclerosis)
This decision is made by a specialized transplant team in coordination with the patient’s treating specialist, weighing the specific evidence for that condition against individual risk factors — it is not a decision made lightly or independent of standard neurology/rheumatology/gastroenterology care.
Frequently asked questions
For some conditions, particularly multiple sclerosis and systemic sclerosis, randomized trials have shown significant long-term benefit, though “cure” is a strong word — outcomes are better described as substantial, durable disease control in appropriately selected patients, not a guaranteed cure for everyone.
No. HSCT involves chemotherapy-based elimination of the existing immune system followed by reinfusion of blood-forming stem cells, and carries meaningfully more risk. Mesenchymal stem cell (MSC) therapy, discussed for other conditions, does not involve this kind of immune ablation and carries a different risk profile.
Risks include infection during the period of immune system reconstitution and a treatment-related mortality risk generally cited around 1–2% in modern series, which is why careful patient selection at specialized centers is essential.
No. The evidence is meaningfully different: randomized trials in MS and systemic sclerosis showed significant benefit, while a randomized trial in refractory Crohn’s disease did not meet its primary endpoint and showed higher-than-expected toxicity. These should not be treated as equivalent evidence.
Related reading
- Common types of autoimmune diseases — full guide
- Crohn’s disease treatment
- Stem cell transplant for CIDP
- Safety & Guarantees FAQ
Have questions about whether this applies to your case? Book a free case review for an honest conversation grounded in the specific evidence for your condition.